
Medicines
SmPC of 30/04/2024
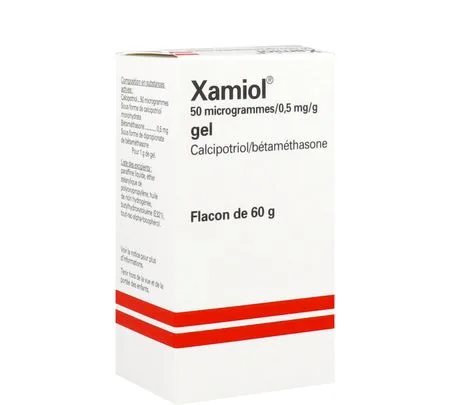
XAMIOL 50 micrograms/0,5 mg/g, gel
Composition
Calcipotriol....................................................................................................................50 micrograms
As calcipotriol monohydrate
Betamethasone...............................................................................................................................0,5 mg
As betamethasone dipropionate
Per 1 g of gel.
Excipients with known effect: 1 g of gel contains 160 micrograms of butylhydroxytoluene and 20 mg of castor oil.
Liquid paraffin, polyoxypropylene stearyl ether, hydrogenated castor oil, butylhydroxytoluene (E321), all-rac-alpha-tocopherol.
Dosage and administration
Dosage
Xamiol gel should be applied once daily to the lesions. The recommended duration of treatment is 4 weeks. If it is necessary to continue or resume treatment after this period, treatment should be continued after medical advice and under regular medical supervision.
When using products containing calcipotriol, the maximum daily dose must not exceed 15 g. The body surface area treated with products containing calcipotriol must not exceed 30 % (see section Warnings and precautions).
All affected areas of the scalp can be treated with Xamiol gel. Usually, an amount between 1 g and 4 g per day is sufficient to treat the scalp (4 g corresponds to one teaspoon).
Special populations
Renal and hepatic impairment
The safety and efficacy of Xamiol gel in patients with severe renal impairment or severe hepatic disorders have not been evaluated.
Paediatric population
The safety and efficacy of Xamiol gel in children under the age of 18 years have not been established. The data currently available in children aged 12 to 17 years are described in sections Adverse effects and Pharmacodynamics but no dosage recommendation can be made.
Method of administration
The bottle should be shaken before use and Xamiol gel applied to the lesions. Xamiol gel should not be applied directly to the face or eyes. Wash hands after use. For optimal effect, it is not recommended to wash the hair immediately after application of Xamiol gel. Xamiol gel should remain on the scalp overnight or during the day.
Contraindications
Hypersensitivity to the active substances or to any of the excipients listed in section Composition.
Xamiol gel is contraindicated in erythrodermic, exfoliative and pustular psoriasis.
Due to the presence of calcipotriol, Xamiol gel is contraindicated in patients with a history of disorders of calcium metabolism (see section Warnings and precautions).
Due to the presence of corticosteroids, Xamiol gel is contraindicated in the following cases: viral (for example herpes or chickenpox), fungal or bacterial skin infections, parasitic infections, skin lesions related to tuberculosis, perioral dermatitis, skin atrophy, striae, fragility of the cutaneous venous network, ichthyosis, acne vulgaris, acne rosacea, rosacea, ulcers and wounds (see section Warnings and precautions).
Warnings and precautions
Effects on the endocrine system
Xamiol gel contains a class III strong group corticosteroid and the simultaneous use of other corticosteroids should be avoided. Adverse effects observed with systemic corticosteroid treatment, such as suppression of the hypothalamic-pituitary axis or the effect on metabolic control of diabetes mellitus, may also occur during topical corticosteroid treatment due to passage into the general circulation.
Application under occlusive dressing should be avoided as it increases systemic absorption of corticosteroids. Application over large areas of damaged skin, on mucous membranes or in skin folds should be avoided as it increases systemic absorption of corticosteroids (see section Adverse effects).
In a study in patients with psoriasis extending to both the scalp and the body, using high doses of Xamiol gel in combination (application to the scalp) and high doses of Daivobet ointment (application to the body), 5 patients out of 32 showed a borderline decrease in their cortisol level in response to corticotropin (ACTH) stimulation after 4 weeks of treatment (see section Pharmacodynamics).
Visual disorders
Visual disturbances may occur with systemic or local corticosteroid therapy. In case of blurred vision or the appearance of any other visual symptom during corticosteroid therapy, an ophthalmological examination is required to look for cataract, glaucoma, or rarer lesions such as central serous chorioretinopathy, as described with systemic or local administration of corticosteroids.
Effects on calcium metabolism
Due to the presence of calcipotriol, hypercalcaemia may occur if the maximum daily dose (15 g) is exceeded. Calcaemia normalises upon discontinuation of treatment. The risk of hypercalcaemia is minimal when the recommendations regarding calcipotriol are followed.
Treatment of more than 30 % of the body surface area should be avoided (see section Dosage and administration).
Local adverse effects
Xamiol gel contains a class III strong group corticosteroid and the simultaneous use of other corticosteroids on the scalp should be avoided.
The skin of the face and the genital region are very sensitive to corticosteroids. The product should not be used in these areas. The patient must be trained in the correct use of the product in order to avoid application and accidental transfer to the face, mouth and eyes. Wash hands after each application to avoid accidental transfer to these areas.
Concomitant skin infections
When lesions become superinfected, they should be treated with antimicrobial therapy. However, if worsening of the infection is observed, corticosteroid treatment should be discontinued (see section Contraindications).
Discontinuation of treatment
Treatment of psoriasis with topical corticosteroids carries a risk of generalised pustular psoriasis or rebound effect on discontinuation. Medical monitoring should therefore be continued after treatment is stopped.
Long-term treatment
With long-term treatment, the risk of local and systemic adverse effects of corticosteroids is increased. Treatment should be discontinued in case of adverse effects related to long-term corticosteroid use (see section Adverse effects).
Use not evaluated
There are no data regarding the use of Xamiol gel in guttate psoriasis.
Concomitant treatment and UV exposure
Daivobet ointment for psoriatic lesions of the body has been used in combination with Xamiol gel for psoriatic lesions of the scalp, but experience is limited regarding the combination of Xamiol gel with other topical anti-psoriatic products applied to the same areas, with other systemically administered anti-psoriatic products or with phototherapy.
During treatment with Xamiol gel, the physician is advised to counsel patients to limit or avoid excessive exposure to natural or artificial light. Topically applied calcipotriol should be combined with UV only if the physician and patient consider that the potential benefits outweigh the potential risks (see section Preclinical safety).
Adverse effects related to excipients
Xamiol gel contains butylhydroxytoluene (E321) and castor oil, which may cause local skin reactions (for example: contact dermatitis, eczema), or irritation of the eyes and mucous membranes.
Fertility, pregnancy and breastfeeding
Pregnancy
There are no sufficiently relevant data regarding the use of Xamiol gel in pregnant women. Animal studies with glucocorticoids have shown reproductive toxicity (see section Preclinical safety), but a number of epidemiological studies (fewer than 300 pregnancies carried to term) have not shown congenital abnormalities in children born to mothers treated with corticosteroids during pregnancy. The potential risk for humans is not known with certainty. Consequently, Xamiol gel should be used during pregnancy only when the potential benefit justifies the potential risk.
Breast-feeding
Betamethasone passes into breast milk, but the risk of an adverse effect in the infant appears unlikely at therapeutic doses. No data are available on the excretion of calcipotriol into breast milk. Caution is required when prescribing Xamiol gel to breastfeeding women.
Fertility
Studies in rats after oral administration of calcipotriol or betamethasone dipropionate have demonstrated no impairment of fertility in males or females (see section Preclinical safety).
Driving and using machines
Xamiol gel has no or negligible effect on the ability to drive vehicles and use machines.
Adverse effects
The estimate of the frequency of adverse reactions is based on a pooled analysis of data from clinical studies, including post-marketing tolerability studies and spontaneous reports.
The most frequently reported adverse reaction during treatment is pruritus.
Adverse reactions are presented by MedDRA system organ class (SOC), and individual adverse reactions are presented within each SOC in order of decreasing frequency. Within each frequency category, adverse reactions are presented in order of decreasing seriousness.
|
Very common |
(≥ 1/10) |
|
Common |
(≥ 1/100 to < 1/10) |
|
Uncommon |
(≥ 1/1 000 to < 1/100) |
|
Rare |
(≥ 1/10 000 to < 1/1 000) |
|
Very rare |
(< 1/10 000) |
|
Not known (frequency cannot be estimated from the available data) |
|
|
Infections and infestations |
|
|
Uncommon ≥ 1/1 000 and < 1/100 |
Skin infection* |
|
Folliculitis |
|
|
Immune system disorders |
|
|
Rare ≥ 1/10 000 and < 1/1 000 |
Hypersensitivity |
|
Eye disorders |
|
|
Uncommon ≥ 1/1 000 and < 1/100 |
Eye irritation |
|
Frequency not known |
Blurred vision** |
|
Skin and subcutaneous tissue disorders |
|
|
Frequent ≥ 1/100 and < 1/10 |
Pruritus |
|
Uncommon ≥ 1/1 000 and < 1/100 |
Exacerbation of psoriasis |
|
Dermatitis |
|
|
Erythema |
|
|
Skin rash*** |
|
|
Acne |
|
|
Skin burning sensation |
|
|
Skin irritation |
|
|
Dry skin |
|
|
Rare ≥ 1/10 000 and < 1/1 000 |
Striae Skin exfoliation |
|
Frequency not known |
Change in hair colour**** |
|
General disorders and administration site conditions |
|
|
Uncommon ≥ 1/1 000 and < 1/100 |
Pain at the application site***** |
|
Rare ≥ 1/10 000 and < 1/1 000 |
Rebound effect |
* Reported skin infections include skin infections of bacterial, fungal and viral origin.
** See section Warnings and precautions.
*** Various types of skin rashes have been reported, such as erythematous rashes and pustular rashes.
**** A transient change in the colouring of white or grey hair to a yellowish colour, at the site of application on the scalp, has been reported.
***** Burns at the application site are included under pain at the application site.
The following adverse effects, considered to be related to the pharmacological class of calcipotriol and betamethasone, are respectively:
Calcipotriol
Adverse effects include reactions at the application site, pruritus, skin irritation, burning and tingling sensation, dry skin, erythema, rash, dermatitis, eczema, worsening of psoriasis, photosensitivity and hypersensitivity reactions including very rare cases of angioedema and facial oedema. Systemic effects after topical application may very rarely occur and cause hypercalcaemia or hypercalciuria (see section Warnings and precautions).
Betamethasone (as dipropionate)
Local reactions may occur after topical use, especially with long-term use, including skin atrophy, telangiectasias, striae, folliculitis, hypertrichosis, perioral dermatitis, contact eczema, depigmentation and colloid milium.
When treating psoriasis with topical corticosteroids, there may be a risk of developing generalised pustular psoriasis.
Systemic reactions after topical application of corticosteroids are rare in adults; however, they may be severe. Suppression of the hypothalamic-pituitary-adrenal axis, cataract, infections, an impact on metabolic control of diabetes mellitus and an increase in intraocular pressure may occur, particularly after prolonged treatment. Systemic effects occur more frequently with application under occlusion (plastic, skin folds), with application over large surfaces and with long-term treatment (see section Warnings and precautions).
Paediatric population
No clinically significant difference has been observed between the tolerability profile in adults and in adolescents. A total of 216 adolescents were treated during 3 open clinical trials. See section Pharmacodynamics for further details concerning these trials.
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website: https://signalement.social-sante.gouv.fr/.
Overdose
Use of doses above the recommended dose may lead to an increase in serum calcium, an effect that is reversible on discontinuation of treatment. Symptoms of hypercalcaemia include polyuria, constipation, muscle weakness, confusion and coma.
Excessive and prolonged use of topical corticosteroids may lead to suppression of the hypothalamic-pituitary axis, resulting in secondary adrenal insufficiency that is usually reversible. In such cases, symptomatic treatment is indicated.
In cases of chronic toxicity, corticosteroid treatment should be discontinued gradually.
One case of misuse has been reported in a patient treated for extensive erythrodermic psoriasis with 240 g of Daivobet ointment per week (corresponding to a daily dose of approximately 34 g) for 5 months (maximum recommended dose 15 g per day); during treatment the patient developed Cushing's syndrome and then pustular psoriasis after abrupt discontinuation of treatment.
Pharmacodynamics
Pharmacotherapeutic group: Antipsoriatics. Other antipsoriatics for topical use, calcipotriol, combinations, ATC code: D05AX52.
Calcipotriol is a vitamin D analogue. Data in vitro suggest that calcipotriol induces differentiation and inhibits proliferation of keratinocytes. This is the proposed mechanism to explain its effects in psoriasis.
Like other topical corticosteroids, betamethasone dipropionate has anti-inflammatory, antipruritic, vasoconstrictive and immunosuppressive properties; however, no curative action has been demonstrated. Treatment under occlusion may increase the effect due to greater penetration into the stratum corneum. The incidence of adverse reactions will therefore be increased. In general, the mechanism of action of the anti-inflammatory activity of topical corticosteroids is not fully known.
The adrenal response to ACTH was determined by measuring cortisolemia in patients with extensive psoriasis of the scalp and body who used up to 106 g per week of Xamiol gel combined with Daivobet ointment. A borderline decrease in cortisol level, 30 minutes after ACTH administration, was observed in 5 patients out of 32 (15,6 %) after 4 weeks of treatment and in 2 patients out of 11 (18,2 %) who extended treatment up to 8 weeks. In all cases, cortisolemia was at a normal level 60 minutes after ACTH administration. No change in calcium metabolism was observed in these patients. Regarding suppression of the hypothalamic-pituitary axis, this study shows that at very high doses Xamiol gel and Daivobet ointment may have a small effect on the hypothalamic-pituitary axis.
The efficacy of once-daily use of Xamiol gel was evaluated in two randomised, double-blind clinical studies of 8 weeks including a total of more than 2 900 patients with scalp psoriasis of at least mild severity according to the Investigator's Global Assessment of disease severity (IGA). The comparators were betamethasone dipropionate in the gel vehicle, calcipotriol in the gel vehicle and (in one of the studies) the gel vehicle alone, all used once daily. Results for the primary endpoint (disease clearance or very mild disease according to the IGA at week 8) showed that Xamiol gel was significantly more effective than the comparators. Results on speed of action based on similar data for week 2 also showed that Xamiol gel was significantly more effective than the comparators.
|
% of patients with clear or almost clear disease |
Xamiol gel (n = 1 108) |
Betamethasone dipropionate (n = 1 118) |
Calcipotriol (n = 558) |
Gel vehicle (n = 136) |
|
week 2 |
53,2 % |
42,8 %1 |
17,2 %1 |
11,8 %1 |
|
week 8 |
69,8 % |
62,5 %1 |
40,1 %1 |
22,8 %1 |
1 Statistically less effective than Xamiol gel (p < 0,001)
Another randomised, single-blind clinical study including 312 patients with scalp psoriasis of at least moderate severity according to the IGA investigated the use of Xamiol gel once daily compared with Daivonex scalp solution twice daily for 8 weeks. Results for the primary endpoint (disease clearance or very mild disease according to the IGA at week 8) showed that Xamiol gel was statistically more effective than Daivonex scalp solution.
|
% of patients with clear or almost clear disease |
Xamiol gel (n = 207) |
Daivonex Scalp solution (n = 105) |
|
week 8 |
68,6 % |
31,4 %1 |
1 Statistically less effective than Xamiol gel (p < 0,001)
A long-term, randomised, double-blind clinical study including 873 patients with scalp psoriasis of at least moderate severity at inclusion (according to the IGA) investigated the use of Xamiol gel compared with calcipotriol in the gel vehicle. Both treatments were applied once daily, intermittently as needed, for up to 52 weeks. Adverse effects possibly related to long-term use of corticosteroids on the scalp were identified blindly by an independent panel of dermatologists. There was no difference in the percentage of patients with such adverse effects between the treatment groups (2,6 % in the Xamiol gel group and 3,0 % in the calcipotriol group; p = 0,73). No cases of skin atrophy were reported.
Paediatric population
Scalp
The effects on calcium metabolism were studied in two open-label, uncontrolled clinical trials of 8 weeks including a total of 109 adolescents aged 12 to 17 years with scalp psoriasis who used up to 69 g per week of Xamiol gel. No cases of hypercalcaemia and no clinically relevant change in calciuria were reported. The adrenal response to ACTH administration was measured in 30 patients; one patient showed a slight decrease in cortisolemia on ACTH administration after 4 weeks of treatment, without clinical manifestation and reversible.
Scalp and body
The effects on calcium metabolism were studied in one open-label, uncontrolled clinical trial of 8 weeks in 107 adolescents aged 12 to 17 years with psoriasis of the scalp and body, who used up to 114,2 g per week of Xamiol gel. No cases of hypercalcaemia and no clinically relevant change in calciuria were reported. The adrenal response to the ACTH test was measured in 31 patients; the cortisol response was decreased after the ACTH test in 5 patients, among whom 2 patients showed only a limited decrease. This decrease was observed after 4 weeks of treatment in 4 patients, and after 8 weeks of treatment in 2 patients, including 1 patient who showed a decrease in cortisolemia after 4 and 8 weeks of treatment. These events were of mild intensity, without clinical manifestation and reversible.
Pharmacokinetics
Systemic exposure to calcipotriol and betamethasone dipropionate due to topical application of Xamiol gel is comparable to that of Daivobet ointment in rats and guinea pigs. Clinical studies with a labelled ointment showed that the systemic absorption of calcipotriol and betamethasone from Daivobet ointment is less than 1 % of the dose (2,5 g) when applied to healthy skin (625 cm2) for 12 hours. Application to psoriatic plaques and under occlusive dressings may increase the absorption of topical corticosteroids. Absorption through diseased skin is approximately 24 %.
After systemic exposure, both active substances - calcipotriol and betamethasone dipropionate - are rapidly and extensively metabolised. Protein binding is approximately 64 %. The plasma elimination half-life after intravenous administration is 5-6 hours. Due to the formation of a depot in the skin, elimination after cutaneous application is on the order of a few days. Betamethasone is metabolised mainly by the liver, but also by the kidneys into glucuronides and sulphate esters. Calcipotriol is excreted via the faeces (rats and guinea pigs) and betamethasone dipropionate via the urine (rats and mice). In rats, tissue distribution studies of radiolabelled calcipotriol and betamethasone dipropionate showed that the kidney and liver had, respectively, the highest levels of radioactivity.
Calcipotriol and betamethasone dipropionate were below the lower limit of quantification in all blood samples from the 34 patients treated for 4 or 8 weeks with both Xamiol gel and Daivobet ointment for extensive psoriasis of the body and scalp. A metabolite of calcipotriol and a metabolite of betamethasone dipropionate were quantifiable in some of the patients.
Preclinical safety
Studies with corticosteroids in animals have shown embryotoxicity (cleft palate, skeletal malformations). In reproductive function studies in rats after long-term oral administration of corticosteroids, prolonged gestation and prolonged, difficult labour were observed. In addition, decreased survival, body weight and weight gain of the offspring were observed. Fertility was not impaired. The relevance of these data for humans is not known.
A dermal carcinogenicity study in mice and an oral carcinogenicity study in rats showed no particular risks of calcipotriol applicable to humans.
Photo(co)carcinogenicity studies in mice suggest that calcipotriol may increase the skin tumour-inducing effect of UV radiation.
A dermal carcinogenicity study in mice and an oral carcinogenicity study in rats showed no particular risks of betamethasone dipropionate applicable to humans. No photocarcinogenicity study has been performed with betamethasone dipropionate.
In local tolerance studies in rabbits, Xamiol gel caused mild to moderate skin irritation and mild, transient eye irritation.
INCOMPATIBILITIES
In the absence of compatibility studies, this medicinal product must not be mixed with other medicinal products.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
Any unused medicinal product or waste material should be disposed of in accordance with local requirements.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Collection.
IMMEUBLE AMPERE E + LA DÉFENSE 34-40 RUE HENRI REGNAULT
92400 COURBEVOIE-LA-DÉFENSE
Tél : 01 30 14 40 00 leo.group@leo-pharma.com
https://www.leo-pharma.fr/
Source: VIDAL · Updated on 11/11/2026. This information does not replace advice from a healthcare professional.