
Medicines
SmPC of 17/04/2024
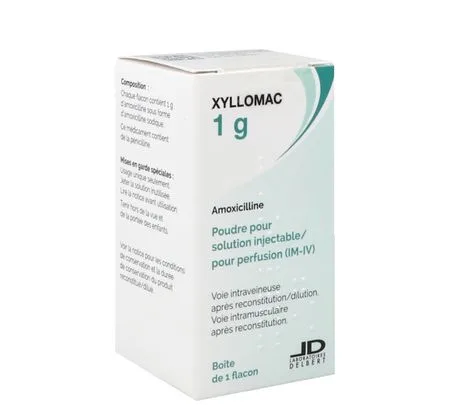
XYLLOMAC 1 g, powder for solution for injection/for infusion (I.M.-I.V.)
Forms and presentations
Powder for solution for injection/for infusion (IM-IV)
Vials containing a sterile white to off-white powder.
Composition
Each vial contains 1 g of amoxicillin in the form of amoxicillin sodium.
Excipient with known effect:
63 mg of sodium (2,74 mmol) per vial.
Indications
XYLLOMAC is indicated for the treatment of the following infections in adults and children (see sections Dosage and administration, Warnings and precautions and Pharmacodynamics) :
- Severe ENT infections (such as mastoiditis, peritonsillar infections, epiglottitis and sinusitis when accompanied by severe systemic signs and symptoms)
- Acute exacerbations of chronic bronchitis
- Community-acquired pneumonia
- Acute cystitis
- Acute pyelonephritis
- Severe dental abscess with cellulitis
- Prosthetic joint infections
- Lyme disease
- Bacterial meningitis
- Bacteraemia associated with, or suspected to be associated with, any of the infections listed above
XYLLOMAC is also indicated for the treatment and prophylaxis of endocarditis.
Official recommendations concerning the appropriate use of antibacterial agents should be taken into account.
Dosage and administration
Dosage
The dose of Xyllomac, powder for solution for injection/for infusion chosen to treat a particular infection should take into account:
- The suspected pathogens and their likely susceptibility to antibacterial agents (see section Warnings and precautions)
- The severity and site of the infection
- The age, weight and renal function of the patient; see below
The duration of treatment will depend on the type of infection and the patient's response to treatment, and should generally be as short as possible. Certain infections require prolonged treatment (see section Warnings and precautions on prolonged treatment).
Adults and children ≥ 40 kg
|
Indication* |
Dose* |
|
Severe ENT infections (such as mastoiditis, peritonsillar infections, epiglottitis and sinusitis when accompanied by severe systemic signs and symptoms) |
750 mg to 2 g every 8 hours, or 2 g every 12 hours, maximum 12 g/day |
|
Acute exacerbations of chronic bronchitis |
|
|
Community-acquired pneumonia |
|
|
Acute cystitis |
|
|
Acute pyelonephritis |
|
|
Severe dental abscess with cellulitis |
|
|
Prosthetic joint infections |
750 mg to 2 g every 8 hours, or 2 g every 12 hours, maximum 12 g/day |
|
Endocarditis prophylaxis |
A single dose of 2 g 30 60 minutes before the procedure |
|
Endocarditis treatment |
1 g to 2 g every 4 to 6 hours, maximum 12 g/day |
|
Bacterial meningitis |
1 g to 2 g every 4 to 6 hours, maximum 12 g/day |
|
Lyme disease (see section Warnings and precautions) |
Late phase (systemic involvement): 2 g every 8 hours |
|
Associated bacteraemia, or suspected of being associated with one of the infections listed in section Indications |
1 g to 2 g every 4, 6 or 8 hours, maximum 12 g/day |
|
* Official therapeutic recommendations for each indication should be taken into account. |
|
Intramuscular route:
Maximum daily dose: 4 g/day.
Maximum single dose: 1 g.
Children < 40 kg
|
Infants > 3 months and children < 40 kg |
Dose* |
|
Indication* |
|
|
Severe ENT infections (such as mastoiditis, peritonsillar infections, epiglottitis and sinusitis when accompanied by severe systemic signs and symptoms) |
20 to 200 mg/kg/day administered in 2 to 4 equal doses not exceeding 25 mg/kg or infusions up to 50 mg/kg per infusion |
|
Community-acquired pneumonia |
|
|
Acute cystitis |
|
|
Acute pyelonephritis |
|
|
Severe dental abscess with cellulitis |
|
|
Endocarditis prophylaxis |
50 mg/kg as a single dose 30 to 60 minutes before the procedure |
|
Endocarditis treatment |
200 mg/kg/day in 3 to 4 equal doses not exceeding 25 mg/kg or infusions up to 50 mg/kg per infusion |
|
Bacterial meningitis |
100 to 200 mg/kg/day in 3 to 4 equal doses not exceeding 25 mg/kg or infusions up to 50 mg/kg per infusion |
|
Lyme disease (see section Warnings and precautions) |
Early phase: 25 to 50 mg/kg/day in three doses for 10 days (10 to 21 days) |
|
Late phase (systemic involvement): 50 mg/kg/day in three doses |
|
|
Associated bacteraemia, or suspected of being associated with one of the infections listed in section Indications |
50 to 150 mg/kg/day administered in 3 equal doses not exceeding 25 mg/kg or infusions up to 50 mg/kg per infusion |
|
* Official therapeutic recommendations for each indication should be taken into account. |
|
|
Newborns ≥ 4 kg and infants under 3 months |
Dose* |
|
Indication* |
|
|
For most infections |
Usual daily dose of 20 to 150 mg/kg/day administered in 3 equal doses not exceeding 25 mg/kg or infusions up to 50 mg/kg per infusion |
|
Endocarditis treatment |
150 mg/kg/day administered in three equal doses not exceeding 25 mg/kg or infusions up to 50 mg/kg per infusion |
|
Bacterial meningitis |
150 mg/kg/day administered in three doses |
|
Lyme disease (see section Warnings and precautions) |
Early phase: 25 to 50 mg/kg/day in 3 doses for 10 days (10 to 21 days) |
|
Late phase (systemic involvement): 50 mg/kg/day in three doses |
|
|
Associated bacteraemia, or suspected of being associated with one of the infections listed in section Indications |
Usual daily dose of 50 to 150 mg/kg/day administered in 3 equal doses not exceeding 25 mg/kg or infusions up to 50 mg/kg per infusion |
|
* Official therapeutic recommendations for each indication should be taken into account. |
|
|
Premature newborns < 4 kg |
Dose* |
|
Indication* |
|
|
For most infections |
Usual daily dose of 20 to 100 mg/kg/day administered in 2 equal doses not exceeding 25 mg/kg or infusions up to 50 mg/kg per infusion |
|
Endocarditis treatment |
100 mg/kg/day administered in two doses |
|
Bacterial meningitis |
100 mg/kg/day administered in two doses |
|
Lyme disease (see section Warnings and precautions) |
Early phase: 25 to 50 mg/kg/day in two doses for 10 days (10 to 21 days) |
|
Late phase (systemic involvement): 50 mg/kg/day in two doses |
|
|
Associated bacteraemia, or suspected of being associated with one of the infections listed in section Indications |
Usual daily dose of 50 to 100 mg/kg/day administered in 2 equal doses not exceeding 25 mg/kg or infusions up to 50 mg/kg per infusion |
|
* Official therapeutic recommendations for each indication should be taken into account. |
|
Intramuscular route:
Maximum daily dosage: 120 mg/kg/day in 2 to 6 equal doses.
Elderly patients
No adjustment necessary; same dosage as for adults.
Patients with renal impairment
|
Adults and children ≥ 40 kg |
Children < 40 kg |
|||
|
GFR (ml/min) |
Intravenous route |
Intramuscular route |
Intravenous route |
Intramuscular route |
|
greater than 30 |
No adjustment |
No adjustment |
No adjustment |
No adjustment |
|
10 to 30 |
1 g immediately, then 500 mg to 1 g twice daily |
500 mg every 12 hours |
25 mg/kg twice daily |
15 mg/kg every 12 hours |
|
less than 10 |
1 g immediately, then 500 mg/day |
500 mg/day in a single dose |
25 mg/kg/day in a single dose |
15 mg/kg/day in a single dose |
Patients undergoing haemodialysis and peritoneal dialysis
Amoxicillin can be removed from the blood circulation by haemodialysis.
|
Haemodialysis |
Peritoneal dialysis |
|||
|
Intravenous route |
Intramuscular route |
Intravenous route |
Intramuscular route |
|
|
Adults and children ≥ 40 kg |
1 g at the end of dialysis, then 500 mg every 24 hours |
500 mg during dialysis, 500 mg at the end of dialysis, then 500 mg every 24 hours |
1 g immediately, then 500 mg/day |
500 mg/day in a single dose |
|
Children < 40 kg |
25 mg/kg immediately and 12,5 mg/kg at the end of dialysis, then 25 mg/kg/day |
15 mg/kg during and at the end of dialysis, then 15 mg/kg every 24 hours |
25 mg/kg/day in a single dose |
15 mg/kg/day in a single dose |
Method of administration
The recommended standard route of administration is the intravenous injection or intravenous infusion. Intramuscular administration should be considered only if the intravenous route is not possible or is less appropriate for the patient.
Intravenous
Xyllomac 1 g, powder for solution for injection/for infusion may be administered either by slow intravenous injection over 3 to 4 minutes directly into a vein, or by drip, or as an infusion over 20 to 30 minutes.
Intramuscular
The maximum recommended single dose in adults and in children weighing ≥ 40 kg is 1 g. Do not inject more than 60 mg/kg at one time in children weighing < 40 kg.
Contraindications
Hypersensitivity to the active substance, to penicillins or to any of the excipients listed in section Composition.
History of severe immediate hypersensitivity reaction (e.g. anaphylaxis) to another beta-lactam (e.g. cephalosporin, carbapenem or monobactam).
Warnings and precautions
Hypersensitivity reactions
Before starting treatment with amoxicillin, a thorough history is required to look for previous hypersensitivity reactions to penicillins, cephalosporins or other beta-lactams (see sections Contraindications and Adverse effects).
Serious and sometimes fatal hypersensitivity reactions (including anaphylactoid reactions and severe cutaneous adverse reactions) have been observed in patients treated with penicillins. Hypersensitivity reactions may also progress to Kounis syndrome, a severe allergic reaction that can lead to myocardial infarction (see section Adverse effects). Such reactions are more likely in patients with a history of penicillin hypersensitivity and in individuals with atopy. If any allergic manifestation occurs, amoxicillin treatment must be stopped and an appropriate alternative treatment instituted.
Drug-induced enterocolitis syndrome (DIES) has been reported mainly in children receiving amoxicillin (see section Adverse effects). DIES is an allergic reaction whose main symptom is prolonged vomiting (1 to 4 hours after drug administration) in the absence of cutaneous or respiratory allergic symptoms. Other symptoms may include abdominal pain, diarrhoea, hypotension or leukocytosis with neutrophilia. Severe cases have been reported, including progression to shock.
Non-susceptible micro-organisms
Amoxicillin is not suitable for the treatment of certain types of infection unless the pathogen has already been documented and is known to be susceptible to amoxicillin, or there is a very high probability that the pathogen is susceptible (see section Pharmacodynamics). This concerns in particular the treatment of patients with urinary tract infections and severe ear, nose and throat infections.
Convulsions
Convulsions may occur in patients with renal impairment or those receiving high doses, or in patients with predisposing factors (e.g. history of convulsions, treated epilepsy, meningeal disorders (see section Adverse effects)).
Renal impairment
In patients with renal impairment, the dose must be adjusted according to the degree of renal impairment (see section Dosage and administration).
Skin reactions
The appearance early in treatment of a generalised febrile erythema associated with pustules may be a symptom of acute generalised exanthematous pustulosis (AGEP) (see section Adverse effects). This reaction requires discontinuation of amoxicillin and contraindicates any subsequent administration of this medicine.
Amoxicillin should be avoided in case of suspected infectious mononucleosis, as the occurrence of a morbilliform rash has been associated with this condition following the use of amoxicillin.
Jarisch-Herxheimer reaction
Jarisch-Herxheimer reactions have been observed following treatment of Lyme disease with amoxicillin (see section Adverse effects). This is a direct consequence of the bactericidal activity of amoxicillin on the bacterium responsible for Lyme disease, the spirochete Borrelia burgdorferi. Patients should be reassured that this is a frequent consequence and generally resolves spontaneously with antibiotic treatment of Lyme disease.
Overgrowth of non-susceptible micro-organisms
Prolonged use may occasionally result in overgrowth of non-susceptible organisms.
Antibiotic-associated colitis has been reported with almost all antibacterial agents: its severity varies from mild to life-threatening (see section Adverse effects).
Therefore, it is important to consider this diagnosis in patients presenting with diarrhoea during or after the administration of any antibiotic. If antibiotic-associated colitis occurs, intake of amoxicillin must be stopped immediately, a doctor must be consulted and appropriate treatment must be initiated. Medicinal products that inhibit peristalsis are contraindicated in this situation.
Prolonged treatment
In case of prolonged treatment, it is recommended to regularly monitor organ function, in particular renal, hepatic and haematopoietic function. Elevation of liver enzymes and changes in blood count have been reported (see section Adverse effects).
Anticoagulants
Rare cases of prolongation of prothrombin time have been reported in patients receiving amoxicillin. Appropriate monitoring must be put in place when anticoagulants are prescribed concurrently. Dose adjustment of oral anticoagulants may be necessary to maintain the desired level of anticoagulation (see sections Interactions and Adverse effects).
Crystalluria
Very rare cases of crystalluria (including acute renal injury) have been observed in patients with low urine output, mainly with parenteral administration. When high doses of amoxicillin are administered, it is advised to maintain adequate fluid intake and urine output to reduce the risk of amoxicillin crystalluria. In patients with urinary catheters, the patency of the catheter should be checked regularly (see sections Adverse effects and Overdose).
Interference with diagnostic tests
High serum and urine levels of amoxicillin are likely to affect certain laboratory tests. Due to high urinary concentrations of amoxicillin, false-positive results are frequent with chemical methods.
When testing for the presence of glucose in urine during treatment with amoxicillin, the enzymatic method with glucose oxidase should be used.
The presence of amoxicillin may interfere with the results of oestriol assays in pregnant women.
Important information about excipients
This medicinal product contains 63 mg (2,74 mmol) of sodium per vial, equivalent to 3,2 % of the WHO recommended maximum daily dietary intake of 2 g of sodium for an adult. To be taken into account in patients on a strict sodium-restricted diet.
Interactions
Probenecid
Concomitant use of probenecid is not recommended. Probenecid decreases the renal tubular secretion of amoxicillin. Concomitant use of probenecid may lead to a prolonged increase in the blood concentration of amoxicillin.
Allopurinol
Concomitant administration of allopurinol during treatment with amoxicillin may increase the likelihood of allergic skin reactions.
Tetracyclines
Tetracyclines and other bacteriostatic medicinal products may interfere with the bactericidal effects of amoxicillin.
Oral anticoagulants
Oral anticoagulants are often administered concomitantly with antibiotics of the penicillin family and no interaction has been reported. However, cases of increased INR have been reported in the literature in patients maintained on acenocoumarol or warfarin during amoxicillin administration. If co-administration is necessary, prothrombin time or INR should be closely monitored when amoxicillin is added or withdrawn. In addition, dose adjustment of oral anticoagulants may be necessary (see sections Warnings and precautions and Adverse effects).
Methotrexate
Penicillins may reduce the excretion of methotrexate and thus increase its toxicity.
Fertility, pregnancy and breastfeeding
Pregnancy
Animal studies have not demonstrated direct or indirect harmful effects on reproduction. Limited data on the use of amoxicillin in pregnant women do not indicate an increased risk of congenital malformations. Amoxicillin may be used during pregnancy if the potential benefits outweigh the potential risks associated with treatment.
Breast-feeding
Amoxicillin is excreted into breast milk in small quantities with a possible risk of sensitisation. Consequently, diarrhoea and fungal infection of the mucous membranes are possible in breast-fed infants and may require discontinuation of breastfeeding. Amoxicillin should only be used during breastfeeding after the treating doctor has assessed the benefit/risk ratio.
Fertility
There are no data on the effects of amoxicillin on human fertility. Animal reproduction studies have shown no effect on fertility.
Driving and using machines
No studies on the ability to drive and use machines have been performed. However, the occurrence of adverse reactions (e.g. allergic reactions, dizziness, convulsions) that may affect the ability to drive or use machines is possible (see section Adverse effects).
Adverse effects
The most common adverse reactions are diarrhoea, nausea and skin rash.
Adverse reactions identified in clinical studies and since the marketing of amoxicillin are listed below by MedDRA system organ class.
The following terminology is used to classify adverse reactions according to their frequency:
Very common (≥ 1/10)
Common (≥ 1/100 to < 1/10)
Uncommon (≥ 1/1 000 to < 1/100)
Rare (≥ 1/10 000 to < 1/1 000)
Very rare (< 1/10 000)
Not known (frequency cannot be estimated from the available data)
|
Infections and infestations |
|
|
Very rare |
Mucocutaneous candidiasis |
|
Blood and lymphatic system disorders |
|
|
Very rare |
Reversible leucopenia (including agranulocytosis or severe neutropenia), reversible haemolytic anaemia and thrombocytopenia. |
|
Prolongation of bleeding time and prothrombin time (INR) (see section Warnings and precautions). |
|
|
Immune system disorders |
|
|
Very rare |
Severe allergic reactions, including angioedema, anaphylaxis, serum sickness and hypersensitivity vasculitis (see section Warnings and precautions). |
|
Frequency not known |
Jarisch-Herxheimer reaction (see section Warnings and precautions) |
|
Nervous system disorders |
|
|
Very rare |
Hyperkinesia, dizziness, convulsions (see section Warnings and precautions). |
|
Frequency not known |
Aseptic meningitis |
|
Cardiac disorders |
|
|
Frequency not known |
Kounis syndrome |
|
Gastrointestinal disorders |
|
|
Data from clinical studies |
|
|
Common* |
Diarrhoea and nausea |
|
Uncommon* |
Vomiting |
|
Post-marketing data |
|
|
Very rare |
Antibiotic-associated colitis (including pseudomembranous colitis and haemorrhagic colitis, see section Warnings and precautions). |
|
Frequency not known |
Drug-induced enterocolitis syndrome |
|
Hepatobiliary disorders |
|
|
Very rare |
Hepatitis and cholestatic jaundice. Moderate increase in AST and/or ALT. |
|
Skin and subcutaneous tissue disorders |
|
|
Data from clinical studies |
|
|
Common* |
Skin rash |
|
Uncommon* |
Urticaria and pruritus |
|
Post-marketing data |
|
|
Very rare |
Cutaneous reactions such as erythema multiforme, Stevens-Johnson syndrome, toxic epidermal necrolysis, bullous and exfoliative dermatitis, acute generalised exanthematous pustulosis (AGEP) and drug reaction with eosinophilia and systemic symptoms (DRESS) (see section Warnings and precautions) |
|
Frequency not known |
Linear IgA dermatosis |
|
Renal and urinary disorders |
|
|
Very rare |
Interstitial nephritis |
|
Frequency not known |
Crystalluria (including acute kidney injury) (see sections Warnings and precautions and Overdose) |
|
* The frequency of these undesirable effects was determined from data from clinical studies involving a total of approximately 6 000 adult and paediatric patients receiving amoxicillin. |
|
Reporting of suspected adverse reactions
Reporting suspected adverse reactions after authorisation of the medicinal product is important. It allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system: National Agency for the Safety of Medicines and Health Products (ANSM) and the network of Regional Pharmacovigilance Centres - Website: https://signalement.social-sante.gouv.fr/
Overdose
Signs and symptoms of overdose
Gastrointestinal symptoms (such as nausea, vomiting and diarrhoea) and disturbances of fluid and electrolyte balance are possible. Amoxicillin-related crystalluria, in some cases leading to renal failure, has been observed (see section Warnings and precautions). Convulsions may occur in patients with renal impairment or those receiving high doses (see sections Warnings and precautions and Adverse effects).
Precipitation of amoxicillin has been observed in urinary catheters, particularly after intravenous administration of high doses. The patency of the catheter should be checked regularly (see section Warnings and precautions).
Management of intoxication
Treatment of gastrointestinal signs is symptomatic and involves particular monitoring of fluid and electrolyte balance.
Amoxicillin can be removed from the blood circulation by haemodialysis.
Pharmacodynamics
Pharmacotherapeutic class: broad-spectrum penicillins, ATC code: J01CA04.
Mechanism of action
Amoxicillin is a semi-synthetic penicillin (an antibiotic of the beta-lactam family), which inhibits one or more enzymes (often referred to as penicillin-binding proteins or PBPs) in the bacterial peptidoglycan biosynthesis pathway, structural components of the bacterial cell wall. Inhibition of peptidoglycan synthesis leads to weakening of the cell wall, often followed by cell lysis and death.
As amoxicillin is subject to degradation by beta-lactamases produced by resistant bacteria, its spectrum of activity when administered alone does not include organisms producing these enzymes.
Pharmacokinetic/pharmacodynamic relationship
The time above the minimum inhibitory concentration (T > MIC) is considered the main parameter of amoxicillin efficacy.
Mechanisms of resistance
The two main mechanisms of resistance to amoxicillin are:
- Inactivation by bacterial beta-lactamases
- Modification of PBPs, which reduces the affinity of the antibacterial agent for its target
Impermeability of bacteria or efflux pump mechanisms may cause or promote bacterial resistance, particularly in Gram-negative bacteria.
Critical concentrations
Critical concentrations for amoxicillin established by EUCAST (European Committee on Antimicrobial Susceptibility Testing) version 5.0.
|
Organism |
MIC susceptibility critical value (mg/L) |
|
|
Susceptible ≤ |
Resistant > |
|
|
Enterobacterales |
81 |
8 |
|
Staphylococcus spp. spp. |
Remark2 |
Remark2 |
|
Enterococcus spp.3 |
4 |
8 |
|
Streptococci of groups A, B, C and G |
Remark4 |
Remark4 |
|
Streptococcus pneumoniae |
Remark5 |
Remark5 |
|
Streptococci of group Viridans |
0.5 |
2 |
|
Haemophilus influenzae |
26 |
26 |
|
Moraxella catarrhalis |
Remark7 |
Remark7 |
|
Neisseria meningitidis |
0.125 |
1 |
|
Gram-positive anaerobes except Clostridium difficile8 |
4 |
8 |
|
Gram-negative anaerobes8 |
0.5 |
2 |
|
Helicobacter pylori |
0,1259 |
0,1259 |
|
Pasteurella multocida |
1 |
1 |
|
Non-species-related critical concentrations10 |
2 |
8 |
|
1 Wild-type Enterobacterales strains are classified as susceptible to aminopenicillins. Some countries prefer to classify wild-type isolates ofE. coli and P. mirabilis in the intermediate category. In that case, the MIC critical value S ≤ 0,5 mg/L should be used. 2 Most staphylococci produce penicillinase and are resistant to amoxicillin. Methicillin-resistant isolates are, with few exceptions, resistant to all antibiotics of the beta-lactam family. 3 Susceptibility to amoxicillin can be inferred from that of ampicillin. 4 The susceptibility of streptococci of groups A, B, C and G to penicillins is inferred from their susceptibility to benzylpenicillin. 5 Critical values concern non-meningeal isolates only. For isolates classified as intermediate to ampicillin, avoid oral treatment with amoxicillin. Susceptibility is inferred from the MIC value of ampicillin. 6 Critical values are based on intravenous administration. Beta-lactamase-positive isolates should be reported as resistant. 7 Beta-lactamase producers should be reported as resistant. 8 Susceptibility to amoxicillin is inferred from susceptibility to benzylpenicillin. 9 Critical values are based on epidemiological cut-off values (ECOFF), which distinguish between wild-type isolates and isolates with decreased susceptibility. 10 Species-independent critical values are based on doses of at least 0,5 g administered 3 to 4 times per day (1,5 to 2 g/day). |
||
The prevalence of resistance may vary by geography and over time for certain species. It is therefore useful to have information on local resistance prevalence, especially for the treatment of severe infections. If necessary, specialist advice should be sought, mainly when the usefulness of the medicine in certain infections may be called into question due to the level of local resistance prevalence.
|
Susceptibility in vitro of microorganisms to amoxicillin |
|
Commonly susceptible species |
|
Aerobic Gram-positive: |
|
Enterococcus faecalis |
|
Streptococcus β-haemolytic (Groups A, B, C and G) |
|
Listeria monocytogenes |
|
Species with variable susceptibility |
|
(acquired resistance > 10 %) |
|
Aerobic Gram-negative: |
|
Escherichia coli |
|
Haemophilus influenzae |
|
Helicobacter pylori |
|
Proteus mirabilis |
|
Salmonella typhi |
|
Salmonella paratyphi |
|
Pasteurella multocida |
|
Aerobic Gram-positive: |
|
Coagulase-negative staphylococci |
|
Staphylococcus aureus£ |
|
Streptococcus pneumoniae |
|
Streptococci of group Viridans |
|
Anaerobic Gram-positive: |
|
Clostridium spp. |
|
Anaerobic Gram-negative: |
|
Fusobacterium spp. |
|
Other: |
|
Borrelia burgdorferi |
|
Naturally resistant species† |
|
Aerobic Gram-positive: |
|
Enterococcus faecium† |
|
Aerobic Gram-negative: |
|
Acinetobacter spp. |
|
Enterobacter spp. |
|
Klebsiella spp. |
|
Pseudomonas spp. |
|
Anaerobic Gram-negative: |
|
Bacteroides spp. (many strains of Bacteroides fragilis are resistant). |
|
Others: |
|
Chlamydia spp. |
|
Mycoplasma spp. |
|
Legionella spp. |
|
† Natural intermediate susceptibility in the absence of an acquired resistance mechanism £ Almost all S. aureus are resistant to amoxicillin due to their production of penicillinase. In addition, all methicillin-resistant strains are resistant to amoxicillin. |
Pharmacokinetics
The pharmacokinetic results from studies in which amoxicillin was administered to groups of healthy volunteers by intravenous bolus injection are presented below.
|
Mean pharmacokinetic parameters |
||||
|
Intravenous bolus injection |
||||
|
Dose administered |
||||
|
Peak serum conc.
|
T 1/2 (h) |
AUC
|
Urinary recovery
|
|
|
500 mg |
32,2 |
1,07 |
25,5 |
66,5 |
|
1 000 mg |
105,4 |
0,9 |
76,3 |
77,4 |
Distribution
About 18 % of total plasma amoxicillin is protein-bound and the apparent volume of distribution is about 0,3 to 0,4 l/kg.
After intravenous administration, amoxicillin has been detected in the gallbladder, abdominal tissue, skin, fat, muscle tissues, synovial and peritoneal fluids, bile and pus. Amoxicillin does not distribute adequately into the cerebrospinal fluid.
Animal studies have not shown significant tissue accumulation of drug-derived substance. Amoxicillin, like the majority of penicillins, can be detected in breast milk (see section Fertility, pregnancy and breastfeeding).
Biotransformation
Amoxicillin is partly excreted in the urine as inactive penicilloic acid, in a proportion of up to 10 to 25 % of the initial dose.
Elimination
The main route of elimination of amoxicillin is renal
Amoxicillin has an average elimination half-life of about one hour and an average total clearance of about 25 l/hour in healthy subjects. About 60 to 70 % of amoxicillin is excreted unchanged in the urine within 6 hours following administration of a single dose of 250 mg or 500 mg of amoxicillin. Various studies have shown that urinary excretion is 50 to 85 % for amoxicillin over a period of 24 hours.
Concomitant use of probenecid delays the excretion of amoxicillin (see section Interactions).
Sex
After oral administration of amoxicillin to healthy men and women, sex does not have a significant effect on the pharmacokinetic characteristics of amoxicillin.
Age
The elimination half-life of amoxicillin in young children aged about 3 months to 2 years is similar to that of older children and adults. In very young children (including premature newborns), during the first week of life, administration should be limited to twice daily due to the immaturity of the renal elimination pathway. Due to an increased likelihood of impaired renal function in elderly patients, the dose should be selected carefully and it may be useful to monitor renal function.
Renal impairment
Total serum clearance of amoxicillin decreases in proportion to the decline in renal function (see section Dosage and administration).
Hepatic impairment
Amoxicillin should be used with caution in patients with hepatic impairment and hepatic function should be monitored regularly.
Preclinical safety
Non-clinical data from conventional studies of safety pharmacology, repeated-dose toxicity, genotoxicity and reproductive and developmental toxicity did not reveal any particular risk for humans.
No carcinogenesis studies have been conducted with amoxicillin.
INCOMPATIBILITIES
This medicinal product must not be mixed with other medicinal products, except those mentioned in section Disposal and handling.
Amoxicillin must not be mixed with blood products, protein fluids such as protein hydrolysates or intravenous lipid emulsions. When prescribed in combination with an aminoglycoside, the antibiotics must not be mixed in the same syringe, infusion bag or transfer set due to loss of aminoglycoside activity under these conditions.
Amoxicillin solutions must not be mixed with infusions containing dextran or bicarbonate.
Shelf life
Powder in vials: 36 months.
Reconstituted vials (for intravenous injection or before dilution for infusion): see section Disposal and handling.
From a microbiological point of view, the reconstituted and diluted solution should be used immediately.
Special storage precautions
This medicinal product does not require any special storage conditions
For storage conditions after reconstitution/dilution of the medicinal product, see section Shelf life.
SPECIAL PRECAUTIONS FOR DISPOSAL AND OTHER HANDLING
Intravenous administration
|
Vial |
Reconstitution solvent (ml) |
|
1 g |
20 |
Water for injections is the usual reconstitution solvent.
A transient pink coloration may or may not develop during reconstitution. Reconstituted solutions are normally colourless or pale yellow. All solutions must be vigorously shaken before injection.
If amoxicillin 250 mg, 500 mg or 1 g is to be administered by direct injection, it must be carried out within 20 minutes of reconstitution.
Preparation of intravenous infusions and stability: Immediately add the reconstituted solution of 1 g (as described above) to 100 ml of infusion fluid (using a small bag or a burette infusion set).
Intravenous amoxicillin may be administered in various solutions for intravenous injection. Provided the reconstitution volumes stated above are respected, antibiotic concentrations are maintained at 20 °C in the following infusion fluids:
|
Dilution solution for intravenous injection |
Stability period at 20 °C |
|
Water for injections Ph. Eur. |
4 h |
|
Sodium chloride intravenous infusion solution at 0,9 % (9 mg/ml) |
4 h |
|
Injectable solution composed of sodium chloride (Ringer's solution) |
2 h |
|
Injectable solution composed of sodium lactate (Ringer's Lactate: Hartmann's solution) |
30 min |
|
Glucose solution at 5 % for injection |
20 min |
|
Sodium chloride solution at 0,18 % (1,8 mg/ml) and glucose 4 % |
30 min |
If the solutions have been reconstituted and kept at room temperature, the infusion must be completed within the time limits stated above.
Administration by intramuscular route
|
Vial |
Reconstitution solvent |
|
250 mg |
1,5 ml of water for injections |
|
500 mg |
2,5 ml of water for injections |
|
1 g |
2,5 ml of water for injections |
The maximum single dose is 1 g.
All solutions must be vigorously shaken before injection and administered immediately after reconstitution.
Any residual antibiotic solution must be discarded.
For single use only.
Prescription, supply and reimbursement
| Marketing authorisation (AMM) |
|
| Price: |
|
Box of 1 vial: Reimbursed by Social Security at 65 %. Collect.
Box of 10 vials: Collect.
49 RUE ROUELLE
75015 PARIS
Tel: 01 46 99 68 20 contact@delbert.fr
http://www.laboratoires-delbert.fr/
Source: VIDAL · Updated on 10/11/2026. This information does not replace advice from a healthcare professional.